Croup (Laryngotracheobronchitis)
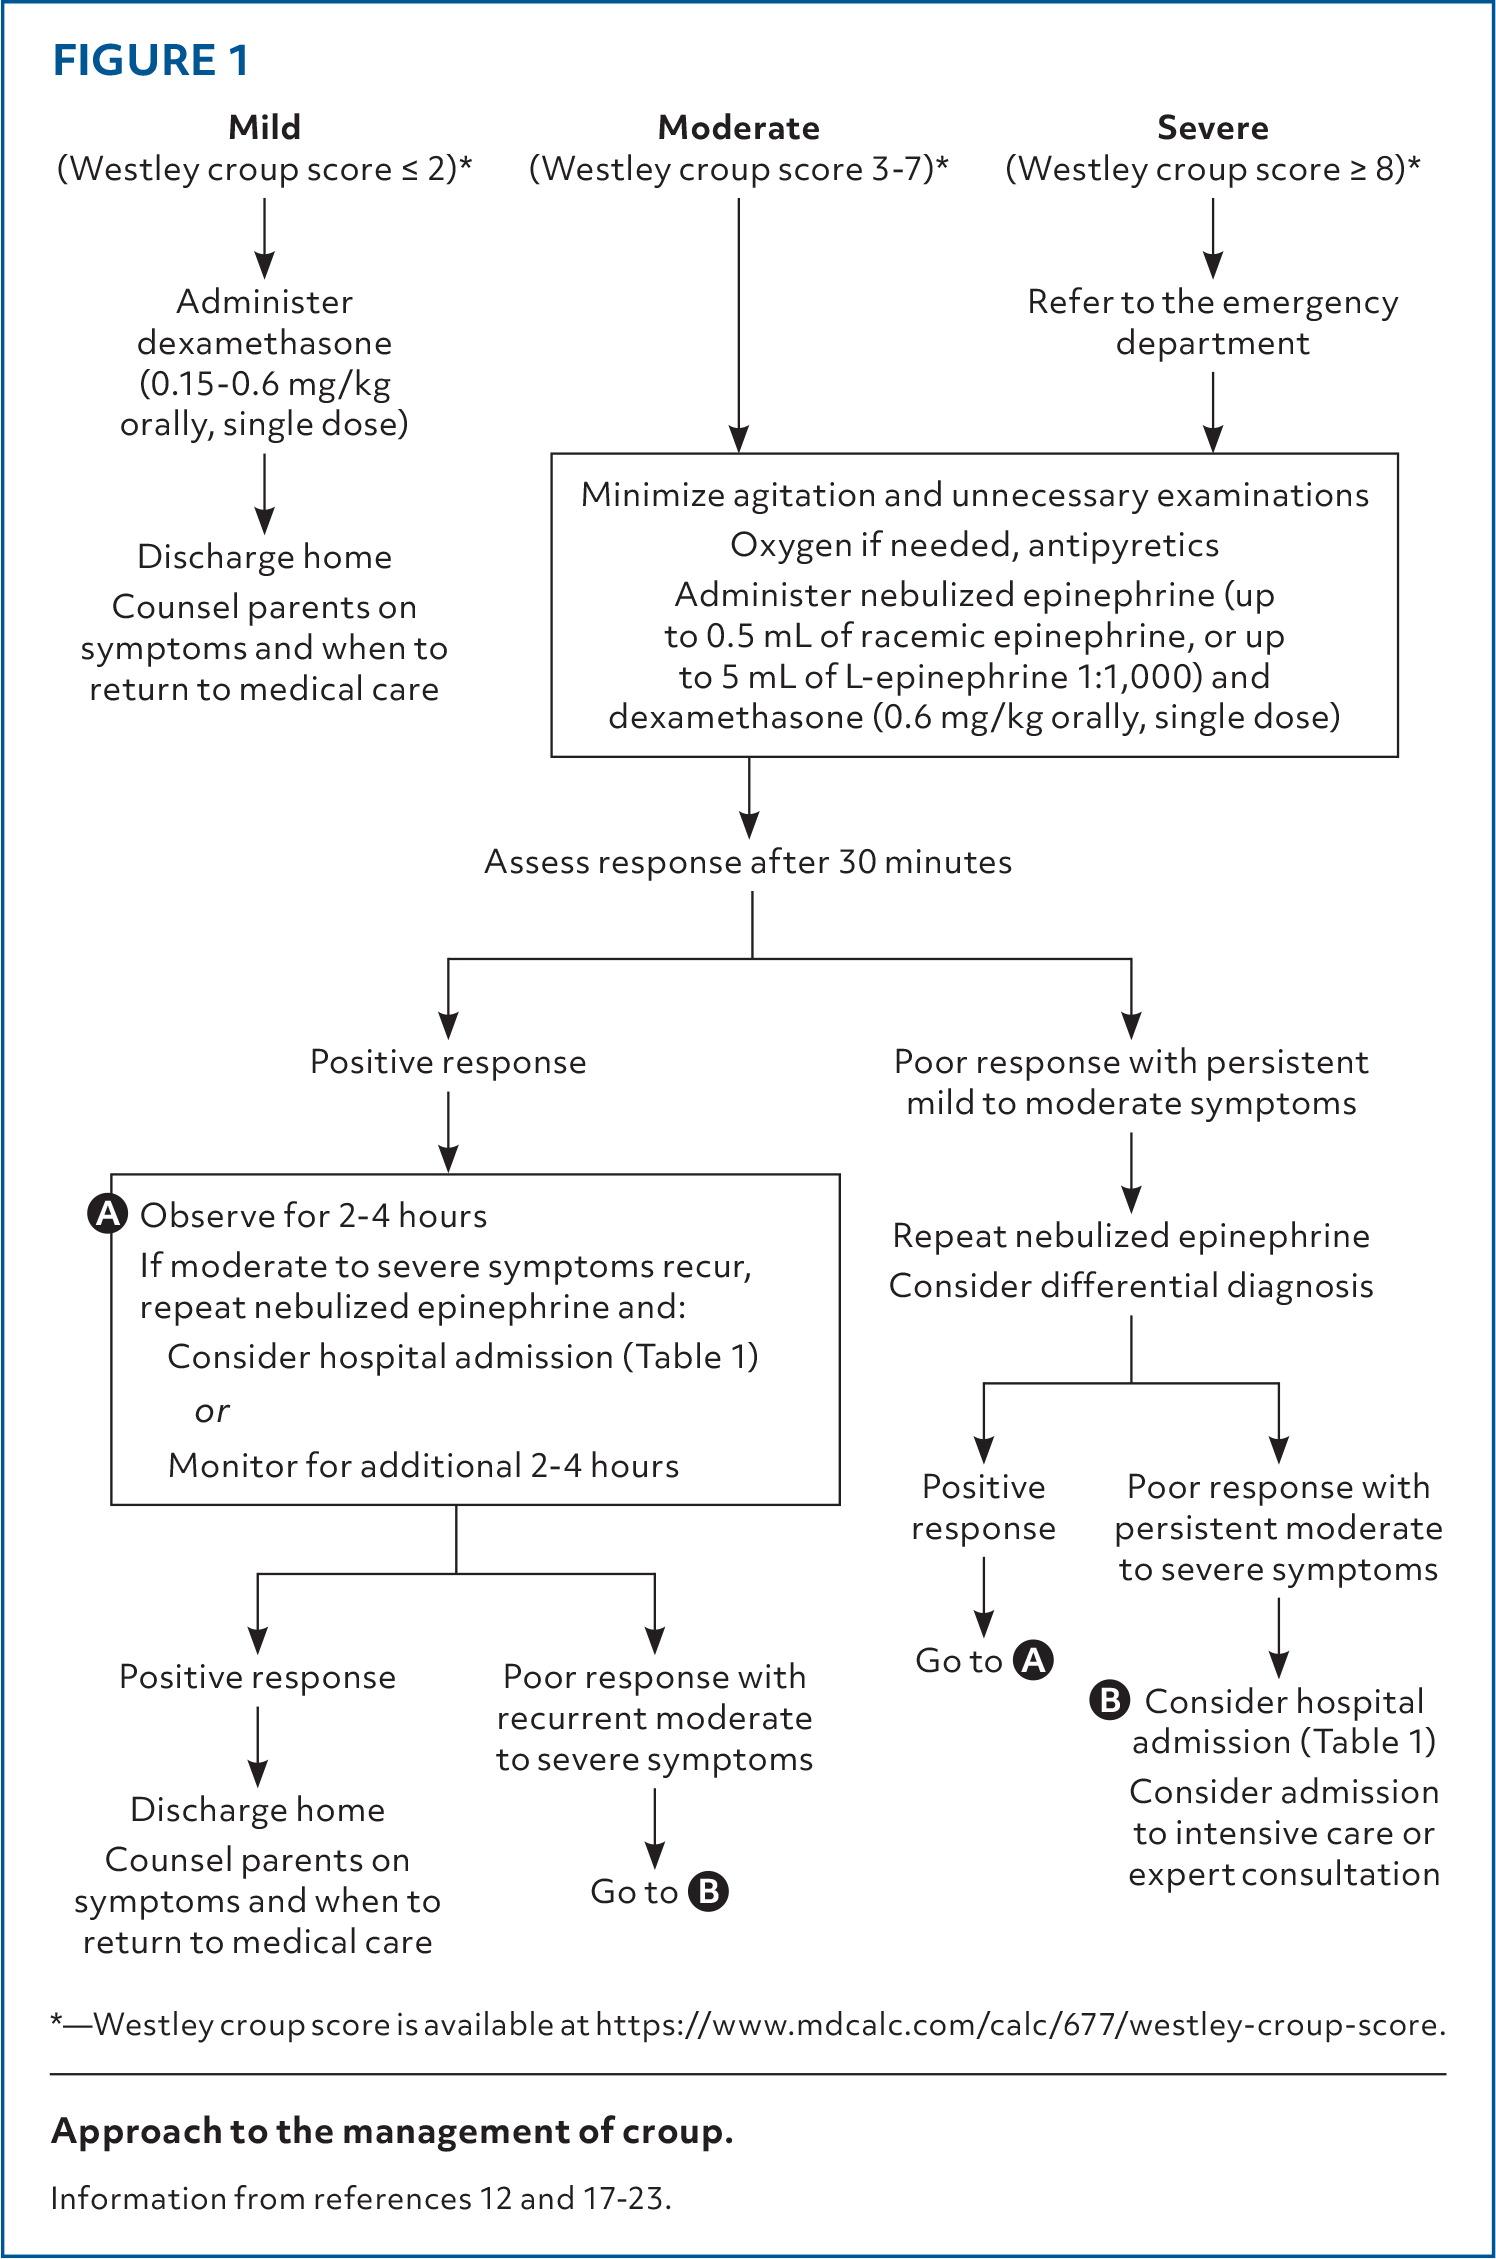
Croup is a common pediatric upper airway illness caused by subglottic inflammation, most often from parainfluenza virus, affecting ~3% of children aged 6 months to 3 years. It presents with the classic triad of barking (seal-like) cough, inspiratory stridor, and hoarseness, with symptoms characteristically worse at night. [1-3] The following figure from the AAFP provides a management algorithm stratified by severity:
History
- HPI essentials: Onset and duration of barking cough, stridor (at rest vs. with agitation only), hoarseness, respiratory difficulty, and fever
- Prodrome: Typically 1–3 days of URI symptoms (rhinorrhea, coryza, low-grade fever) before the barking cough begins [3]
- Timing: Abrupt onset at night is classic; symptoms often worsen with agitation and crying [3-4]
- Severity markers: Ability to drink/eat, sleep disruption, activity level, degree of respiratory distress
- Prior episodes: Recurrent croup (≥2 episodes/year) should raise concern for underlying anatomic abnormality, GERD, or atopy [1]
- Important negatives: Choking/foreign body ingestion history, drooling, dysphagia, immunization status (Hib), toxic appearance, rash
Alarm Features
- Stridor at rest (indicates moderate-to-severe obstruction)
- Suprasternal/sternal retractions, nasal flaring, accessory muscle use
- Cyanosis or SpO₂ <92%
- Lethargy, altered consciousness, or decreased responsiveness [3][5]
- Drooling, inability to swallow, tripod positioning → think epiglottitis [1][6]
- Toxic appearance, high fever, failure to respond to standard therapy → think bacterial tracheitis [6]
- Sudden onset without prodrome or fever → think foreign body or angioedema [6-7]
- Biphasic stridor (inspiratory + expiratory) suggests more severe or fixed obstruction
Medications
- First-line — Corticosteroids (all severities):
- Moderate-to-severe — Nebulized epinephrine:
- Not indicated: Antibiotics (unless bacterial superinfection suspected), albuterol, cough suppressants
- No proven benefit: Humidified mist therapy [8-9]
- Adjunct with emerging evidence: Exposure to outdoor cold air (<50°F) for 30 minutes combined with dexamethasone may reduce symptoms in mild-to-moderate croup [1]
Diet
- Encourage clear fluids to maintain hydration; avoid forcing oral intake if child is in significant distress
- Small, frequent sips preferred over large volumes
- No specific dietary triggers or restrictions apply
- Assess for dehydration if poor oral intake has been prolonged
Review of Systems
- Respiratory: Cough character (barking vs. productive), stridor timing, work of breathing, apneic episodes
- ENT: Hoarseness, drooling, dysphagia, sore throat, ear pain
- Constitutional: Fever (typically low-grade; high fever → consider bacterial tracheitis/epiglottitis), irritability, lethargy
- GI: Vomiting (from coughing paroxysms), feeding difficulty, reflux symptoms (if recurrent croup)
- Skin: Rash (consider measles croup in unimmunized, urticaria if angioedema)
Collateral History and Family History
- Collateral: Caregiver description of cough sound, witnessed choking events, sick contacts, daycare exposure
- Family history: Atopy, asthma, recurrent croup in siblings (associated with airway hyperreactivity) [1][3]
- Immunization status: Hib vaccine (epiglottitis risk in under-immunized), diphtheria vaccine (laryngeal diphtheria in unimmunized) [1][6]
- Social context: Daycare attendance (viral exposure), secondhand smoke exposure
Risk Factors
- Age: Peak incidence in the second year of life; range 6 months to 6 years [2-3]
- Sex: Male predominance (1.5:1) [3]
- Season: Peak in autumn/winter (October–November) [1][3]
- Prematurity or history of neonatal intubation (subglottic stenosis risk)
- Underlying airway abnormalities: Subglottic stenosis, tracheobronchomalacia, laryngomalacia [1]
- Atopy/asthma: Children with ≥2 episodes of croup before age 4 have high incidence of asthma and allergies [3]
- GERD — strongly associated with recurrent croup [1]
Differential Diagnosis
Cannot-miss dangerous diagnoses: [1][6-7]
- Epiglottitis — High fever, drooling, dysphagia, tripod position, muffled voice, NO barking cough; under-immunized for Hib
- Bacterial tracheitis — Toxic-appearing child, high fever, worsening after initial URI, fails to respond to nebulized epinephrine; most common pathogen is S. aureus
- Foreign body aspiration — Sudden onset, no prodrome/fever, history of choking; no barking cough
- Retropharyngeal abscess — Neck stiffness, dysphagia, drooling, unilateral cervical adenopathy
- Peritonsillar abscess — Trismus, "hot potato" voice, unilateral tonsillar swelling
Other considerations:
- Angioedema/allergic reaction — Rapid onset, possible urticaria, history of allergy
- Laryngeal diphtheria — Unimmunized, gradual onset, pharyngeal membrane
- Subglottic stenosis — Recurrent or atypical presentations
- Laryngotracheobronchopneumonia — Lower airway signs (crackles, wheezing), radiographic pneumonia [7]
Past Medical History
- Previous croup episodes (frequency, severity, need for intubation)
- History of neonatal intubation or airway surgery (subglottic stenosis)
- Asthma, reactive airway disease, atopy
- GERD
- Congenital airway anomalies (laryngomalacia, tracheomalacia, vascular ring)
- Immunodeficiency (consider atypical infections)
- Immunization history (Hib, diphtheria)
Physical Exam
- Vitals: Tachypnea, tachycardia (may reflect distress or fever); SpO₂ (cyanosis is a late finding); temperature
- General: Level of distress, position of comfort, ability to interact, consolability — keep the child calm; agitation worsens obstruction [3]
- Airway/ENT: Barking cough quality, inspiratory stridor (at rest vs. with agitation), hoarseness; look for drooling or dysphagia (suggests epiglottitis)
- Chest: Suprasternal, intercostal, and subcostal retractions; air entry (decreased = severe); biphasic stridor
- Abdomen: Assess hydration status
- Skin: Color (pallor, cyanosis), rash
Westley Croup Score (0–17 points) — used for severity stratification: [3][7]
- Mild: Westley score <4 (~85% of cases) — barking cough, no stridor at rest
- Moderate: Westley score 4–6 — stridor at rest, mild retractions
- Severe: Westley score >6 — stridor at rest, marked retractions, decreased air entry, ± altered consciousness [3][7]
Lab Studies
- Labs are typically unnecessary for diagnosis of croup [1-2]
- Viral cultures and rapid antigen testing have minimal impact on management and are not routinely recommended [2]
- If bacterial superinfection suspected (toxic appearance, failure to improve): CBC with differential (leukocytosis with bandemia), blood cultures, CRP [7]
- If dehydration is a concern: BMP
- Rapid influenza testing may be considered in appropriate season if it would change management [7]
Imaging
- Imaging is not routinely indicated for typical croup [1-2]
- AP neck radiograph: Classic "steeple sign" (subglottic narrowing) — sensitivity is limited; useful when diagnosis is uncertain [2][10]
- Lateral neck radiograph: Helpful to evaluate for epiglottitis (thumbprint sign), retropharyngeal abscess (prevertebral soft tissue widening), or foreign body [6-7]
- Chest radiograph: Consider if lower airway involvement suspected (laryngotracheobronchopneumonia) [7]
- CT neck with contrast: Reserved for suspected deep space neck infections (retropharyngeal/peritonsillar abscess)
- Avoid imaging in severe distress — prioritize airway management
Special Tests
- Westley Croup Score: Primary severity stratification tool (see Physical Exam section above) [3][7]
- Pulse oximetry: Continuous monitoring in moderate-to-severe cases
- Laryngoscopy/bronchoscopy: Reserved for atypical presentations, recurrent croup, or suspected anatomic abnormality; NOT indicated in acute setting unless airway intervention needed [1-2]
- Triple endoscopy (laryngoscopy, bronchoscopy, esophagoscopy): Recommended for children <3 years with recurrent croup and high suspicion for airway abnormality; most common findings include reflux changes, subglottic stenosis, and tracheobronchomalacia [1]
ECG
- ECG is not routinely indicated in croup
- Consider if there is unexplained tachycardia out of proportion to fever/distress, or if multiple doses of nebulized epinephrine have been administered (monitor for arrhythmia)
- Continuous cardiorespiratory monitoring is appropriate for children receiving nebulized epinephrine
Assessment
Croup is a clinical diagnosis based on the characteristic barking cough, inspiratory stridor, and hoarseness, typically preceded by 1–3 days of URI symptoms in a child aged 6 months to 3 years. [1-3] Approximately 85% of cases are mild, with only 1–8% requiring hospitalization and <3% of admitted patients requiring intubation. [7][9]
Severity stratification drives management
- Mild (Westley <4): Barking cough, no stridor at rest → dexamethasone alone, discharge home
- Moderate (Westley 4–6): Stridor at rest, chest wall retractions → dexamethasone + nebulized epinephrine, observe
- Severe (Westley >6): Marked retractions, decreased air entry, altered consciousness → aggressive treatment, possible ICU [3][7]
Complications to consider: respiratory failure requiring intubation, bacterial superinfection (laryngotracheobronchitis/laryngotracheobronchopneumonia), pulmonary edema (rare, post-obstructive). [7]
Treatment Plan
All severities — Corticosteroids
- Dexamethasone 0.6 mg/kg PO × 1 dose (max 12 mg) — standard of care [1][4][7]
- Can be given IM or IV if unable to tolerate PO
- A Cochrane review of 43 RCTs (4,565 children) confirmed glucocorticoids reduce symptoms at 2 hours, shorten hospital stays, and reduce return visits (NNT = 7) [4][11]
Moderate-to-severe — Add nebulized epinephrine
- Racemic epinephrine 0.5 mL of 2.25% in 4.5 mL NS, or L-epinephrine 5 mL of 1:1000 via nebulizer [7]
- May repeat as needed for persistent/recurrent stridor [5]
- Observe 2–4 hours post-treatment for symptom recurrence [1]
Severe/impending respiratory failure
- Supplemental oxygen for hypoxia
- Repeated nebulized epinephrine
- Consider heliox (70:30 helium-oxygen) — limited evidence of benefit but may reduce work of breathing [3]
- Prepare for advanced airway management if deteriorating [5]
- If bacterial superinfection suspected: IV antibiotics (vancomycin + cefotaxime) and likely intubation [7]
Adjunctive
- Keep child calm — minimize agitation (worsens obstruction)
- Cold outdoor air exposure (<50°F for 30 min) combined with dexamethasone may reduce symptoms in mild-to-moderate croup [1]
- Humidified mist has no proven benefit [8-9]
Disposition
- Discharge home (mild croup): Westley score <2 after treatment, no stridor at rest, tolerating PO, reliable caregiver, close follow-up available [12]
- ED observation: Westley score 2–5 after dexamethasone; observe for improvement over 2–4 hours; if improved and no stridor at rest, may discharge [6]
- Admission criteria: [1][6]
- Persistent stridor at rest after corticosteroids and epinephrine
- Requiring ≥2 doses of nebulized epinephrine
- SpO₂ <92% on room air
- Toxic appearance or altered mental status
- Inability to tolerate oral fluids
- Unreliable follow-up or caregiver concerns
- Suspected bacterial tracheitis, epiglottitis, or other dangerous alternative diagnosis
- ICU admission: Severe croup unresponsive to treatment, impending respiratory failure, need for repeated epinephrine, or intubation [7]
- Specialist consultation: ENT or pediatric pulmonology for recurrent croup, suspected anatomic abnormality, or need for airway intervention [1]
Follow Up / Return Precautions
- Follow-up: Primary care within 24–48 hours for moderate cases; sooner if any concerns
- Expected course: Barking cough typically resolves within 48 hours in 60% of children; total illness duration 3–7 days [3]
- Return immediately for:
- Stridor at rest or worsening breathing difficulty
- Drooling, inability to swallow
- Cyanosis or color change
- Lethargy, decreased responsiveness
- High fever with toxic appearance
- Inability to drink fluids
- Parent counseling:
- Symptoms are typically worst on nights 1–2 and improve thereafter
- Cool night air may provide temporary relief
- Keep child calm — crying and agitation worsen stridor
- Dexamethasone effect lasts ~48–72 hours; additional doses are generally not recommended [7]
- Recurrent episodes (≥2/year) warrant further evaluation for underlying conditions [1]
References
1. Croup: Rapid Evidence Review. — Cooke A, Conway S, Griffin L. American Family Physician. 2026.
2. Croup: Diagnosis and Management. — Smith DK, McDermott AJ, Sullivan JF. American Family Physician. 2018.
3. Heliox for Croup in Children. — Moraa I, Sturman N, McGuire TM, van Driel ML. The Cochrane Database of Systematic Reviews. 2021.
4. Acute Upper Airway Obstruction. — Eskander A, de Almeida JR, Irish JC. The New England Journal of Medicine. 2019.
5. Preparation for Pediatric Emergencies in the Office: Technical Report. — Cantrell P, Hoffmann J, Yuknis M, et al. Pediatrics. 2026.
6. Croup. — Bjornson CL, Johnson DW. Lancet. 2008.
7. Croup. — Cherry JD. The New England Journal of Medicine. 2008.
8. Nebulized Epinephrine for Croup in Children. — Bjornson C, Russell K, Vandermeer B, Klassen TP, Johnson DW. The Cochrane Database of Systematic Reviews. 2013.
9. Croup: An Overview. — Zoorob R, Sidani M, Murray J. American Family Physician. 2011.
10. Initial Radiographic Tracheal Ratio in Predicting Clinical Outcomes in Croup in Children. — Yang WC, Hsu YL, Chen CY, et al. Scientific Reports. 2019.
11. Glucocorticoids for Croup in Children. — Gates A, Johnson DW, Klassen TP. JAMA Pediatrics. 2019.
12. Westley Score and Clinical Factors in Predicting the Outcome of Croup in the Pediatric Emergency Department. — Yang WC, Lee J, Chen CY, Chang YJ, Wu HP. Pediatric Pulmonology. 2017.
Figure
More from Deep Dive
Reviewed by Dr. Lucas Mastropaolo. SymptomDx is an educational tool for medical professionals — it does not replace clinical judgment. Verify all clinical data and drug dosages with authoritative sources.