Nephrotic Syndrome Flare
A nephrotic syndrome (NS) flare/relapse is defined as the recurrence of nephrotic-range proteinuria (uPCR ≥2 g/g or dipstick ≥3+ for 3 consecutive days) in a patient who had previously achieved complete remission. [1-2] Life-threatening complications occur during 1–4% of flares, particularly when albumin is <20–25 g/L. [3] Relapse rates are high: 70–80% of adults with minimal change disease (MCD) relapse, with average time to relapse ~22 weeks. [4] In children, ~50% of steroid-sensitive patients develop frequently relapsing or steroid-dependent disease. [5]
History
- Onset and progression of edema — periorbital (morning), lower extremity, scrotal/labial, ascites [3]
- Foamy/frothy urine — often the first symptom noticed by patients [3]
- Antecedent upper respiratory infection — a common relapse trigger [6]
- Timing relative to steroid taper or discontinuation of immunosuppressive agents [1]
- Prior relapse frequency, steroid responsiveness, and time to last remission [1]
- Weight gain trajectory — quantify over days to weeks
- Medication adherence — particularly to steroids, CNIs, or MMF [7]
- Abdominal pain (peritonitis, renal vein thrombosis), dyspnea (pleural effusion, PE), headache (cerebral venous sinus thrombosis) [6]
- Decreased urine output — suggests AKI or hypovolemia [8]
Alarm Features
- Shock/hypotension — hypovolemia from protein losses, aggravated by diuretics or sepsis; warrants urgent albumin infusion [3]
- Fever with abdominal pain — spontaneous bacterial peritonitis (SBP), reported in 1.5–16% of relapses [3]
- Unilateral leg swelling, pleuritic chest pain, dyspnea — DVT/PE; VTE risk is ~27% in adults with NS [2-3]
- Headache with neurological signs — cerebral venous sinus thrombosis [6]
- Oliguria/anuria — AKI complicating NS, especially in adults >50 with severe hypoalbuminemia [8]
- Severe respiratory distress — massive pleural effusion or pulmonary edema from albumin infusion [3]
- Albumin <2.0 g/dL — threshold for life-threatening complications including thrombosis and infection [2-3]
Medications
Relevant contributors and cautions:
- NSAIDs — can cause NS (interstitial nephritis with MCD) and worsen renal function; avoid during flares [6]
- Bisphosphonates, lithium, D-penicillamine, heavy metals — secondary causes of NS [6]
- DOACs (factor Xa inhibitors, direct thrombin inhibitors) — have significant albumin binding and are lost in nephrotic urine; pharmacokinetics are poorly studied; not recommended for anticoagulation in NS per KDIGO/KDOQI [7]
- Diuretics — use cautiously; can precipitate hypovolemia and AKI, especially in the setting of severe hypoalbuminemia [8-9]
Common treatments during flare:
- Loop diuretics (furosemide, bumetanide, torsemide) — first-line for edema; give BID; higher doses needed due to albumin binding in tubular lumen [2][9]
- Thiazide add-on (metolazone, HCTZ) — for diuretic resistance; give 2–5 hours before loop diuretic [2]
- ACEi/ARB — antiproteinuric effect; continue unless hypotensive or AKI [10]
- Corticosteroids — mainstay of relapse treatment (see Treatment Plan below) [1-2]
- Anticoagulation — heparin or warfarin if VTE risk > bleeding risk; use the UNC online tool for risk assessment [2][7]
Diet
- Sodium restriction: 1.5–2 g/day (60–90 mmol/day) during flares to manage edema and optimize diuretic response [2]
- Fluid restriction: recommended if Na <130 mEq/L (after excluding pseudohyponatremia from hyperlipidemia) [3]
- Protein intake: moderate protein intake (0.8–1 g/kg/day in adults); excessive protein does not replace urinary losses and may worsen hyperfiltration
- Avoid high-sodium processed foods during active disease
- Long-term: lipid-lowering diet given associated hyperlipidemia [11]
Review of Systems
- Constitutional: fatigue, weight gain, malaise
- Respiratory: dyspnea (pleural effusion, PE), cough
- GI: abdominal pain/distension (ascites, SBP), nausea, decreased appetite
- GU: foamy urine, decreased urine output, hematuria (suggests atypical etiology)
- MSK: joint pain, rash (lupus nephritis)
- Neuro: headache, vision changes (cerebral venous thrombosis, posterior reversible encephalopathy syndrome)
- Skin: periorbital puffiness, scrotal/labial edema
- Infectious: fever, URI symptoms (relapse trigger), varicella exposure in immunosuppressed patients [3]
Collateral History and Family History
- Family history of NS or kidney disease — suggests genetic/hereditary forms, especially in steroid-resistant disease [3]
- Consanguinity — increases likelihood of monogenic NS [3]
- Medication compliance history from caregivers (especially in pediatric patients)
- Recent infections or sick contacts — URI is the most common relapse trigger [6-7]
- Vaccination status — particularly pneumococcal, meningococcal, varicella in immunosuppressed patients [3]
- Social context: access to medications, ability to monitor urine dipstick at home
Risk Factors
- Steroid-dependent or frequently relapsing disease (≥2 relapses in first 6 months or ≥3/year) [1]
- Upper respiratory tract infections — most common trigger [6]
- Steroid taper or discontinuation — relapses commonly occur during or within 14 days of stopping steroids [1]
- Non-adherence to immunosuppressive therapy
- Underlying histology: MCD has highest relapse rate (~70–80% in adults); membranous nephropathy has highest VTE risk [2][4]
- VTE risk factors during flare: albumin <2.5 g/dL, female sex, BMI ≥30, AKI, sepsis, lupus nephritis, IV corticosteroid use, immobility [2][12]
- Age >50 (adults) — increased risk of AKI complicating MCD [8]
Differential Diagnosis
When a known NS patient presents with worsening edema, confirm true relapse vs. alternative causes:
- True NS relapse — recurrence of nephrotic-range proteinuria with hypoalbuminemia
- Heart failure — elevated JVP, S3, pulmonary crackles; BNP elevated; proteinuria typically subnephrotic
- Hepatic cirrhosis/liver failure — stigmata of liver disease, ascites predominant, low albumin from synthetic failure
- Medication-induced NS — NSAIDs, bisphosphonates, lithium [6]
- Secondary glomerulonephritis — lupus nephritis (low C3/C4, ANA+), membranoproliferative GN, IgA nephropathy; suspect if hematuria, hypertension, or low complement [3][6]
- Renal vein thrombosis — flank pain, hematuria, acute worsening of proteinuria; more common in membranous nephropathy [2]
- Infection-triggered transient proteinuria vs. true relapse — confirm with 3 consecutive days of dipstick ≥3+ [1]
- Progression to FSGS — 10–30% of adults initially diagnosed with MCD may have underlying FSGS on repeat biopsy [4]
Past Medical History
- Number and timing of prior relapses — defines frequently relapsing vs. infrequently relapsing vs. steroid-dependent disease [1]
- Steroid responsiveness — steroid-sensitive vs. steroid-resistant [1]
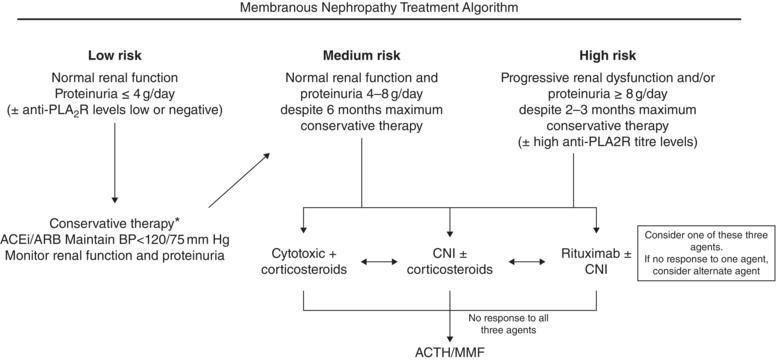
- Prior immunosuppressive agents used and response (cyclophosphamide, CNIs, MMF, rituximab) [1][13]
- Prior complications: VTE, AKI, SBP, steroid side effects (osteoporosis, diabetes, cataracts, growth failure in children) [7]
- Renal biopsy results — histologic subtype (MCD, FSGS, membranous) [10]
- Baseline renal function and prior creatinine values
- Comorbidities: diabetes, hypertension, obesity, thrombophilia
Physical Exam
- Vitals: blood pressure (hypertension or hypotension), heart rate (tachycardia if hypovolemic), weight (compare to dry weight), temperature (infection)
- General: cushingoid features (chronic steroid use), overall volume status
- Eyes: periorbital edema (often first sign, worse in morning) [3]
- Lungs: decreased breath sounds (pleural effusion), crackles (pulmonary edema)
- Cardiovascular: JVP assessment, S3 (to exclude heart failure)
- Abdomen: ascites (shifting dullness, fluid wave), tenderness/guarding (SBP), hepatomegaly
- Extremities: pitting edema (lower extremity, sacral), unilateral swelling (DVT)
- Genitalia: scrotal/labial edema [3]
- Skin: skin breakdown from severe edema, striae (steroid use)
- Neuro: mental status, focal deficits (cerebral venous thrombosis)
Lab Studies
Recommended labs during a flare:
- Urinalysis with microscopy — confirm ≥3+ protein; assess for hematuria, casts [3][6]
- Spot urine protein-to-creatinine ratio (uPCR) — quantify proteinuria (≥2 g/g = nephrotic range) [1]
- Serum albumin — severity marker; <2.5 g/dL significantly increases VTE risk [2]
- BMP (creatinine, BUN, electrolytes) — assess renal function, hyponatremia [3]
- CBC — infection, hemoconcentration
- Lipid panel — hyperlipidemia is expected [10]
- Coagulation studies — if VTE suspected
- Blood cultures — if febrile or concern for SBP/sepsis
Rule-out labs (if atypical features or first presentation):
- Complement C3/C4, ANA, anti-dsDNA, ANCA, ASO titer — if hematuria, hypertension, or systemic symptoms [3][6]
- Hepatitis B/C, HIV — secondary causes [6]
- Anti-PLA2R antibodies — if membranous nephropathy suspected [14]
Monitoring parameters:
- Daily urine dipstick until remission, then at least twice weekly [3]
- Blood pressure and body weight twice weekly during relapse [3]
Imaging
- Renal ultrasound — consider if reduced eGFR, hematuria, abdominal pain, or concern for renal vein thrombosis; also to exclude structural abnormalities [3]
- Chest X-ray — if dyspnea, to evaluate for pleural effusion or pulmonary edema
- Doppler ultrasound of renal veins/lower extremities — if clinical suspicion for DVT or renal vein thrombosis [2]
- CT pulmonary angiography — if PE suspected
- Routine imaging is not needed for uncomplicated relapses in patients with known NS [15]
Special Tests
- Urine dipstick — point-of-care confirmation of relapse (≥3+ for 3 consecutive days) [1]
- UNC Bleeding Risk Tool (www.med.unc.edu/gntools/bleedrisk.html) — online calculator to weigh VTE risk vs. bleeding risk for anticoagulation decisions in NS [2][7]
- Renal biopsy — indicated if atypical features (macroscopic hematuria, low C3, sustained hypertension, systemic symptoms), steroid resistance, or AKI not attributed to hypovolemia [3]
- Genetic testing — for congenital NS, primary steroid-resistant NS, or suspected syndromic forms [3]
- DEXA scan — every 12–18 months if prolonged or high cumulative steroid exposure [3]
- Ophthalmologic exam — yearly for cataracts/glaucoma screening with chronic steroid use [3]
ECG
- Indications: chest pain, dyspnea, tachycardia, or suspected PE/VTE
- Assess for right heart strain pattern (S1Q3T3, right axis deviation, RBBB) if PE suspected
- Electrolyte-related changes: hypokalemia (U waves, QT prolongation) from diuretic use; hyperkalemia if AKI develops
- Not routinely required for uncomplicated NS relapse
Assessment
A nephrotic syndrome flare represents the recurrence of heavy proteinuria and hypoalbuminemia in a previously remitting patient, most commonly triggered by infection or steroid taper. Severity stratification is driven by the degree of hypoalbuminemia — albumin <2.0–2.5 g/dL marks the threshold for life-threatening complications including VTE (up to 27% in adults), AKI, and serious infection. [2-3][8]
Key considerations:
- Typical presentation: progressive edema, weight gain, foamy urine, fatigue
- Atypical features warranting further workup: hematuria, hypertension, low complement, systemic symptoms, AKI not from hypovolemia [3]
- Complications to anticipate: VTE (DVT, renal vein thrombosis, PE), SBP (especially in children), AKI (diuretic-induced hypovolemia or intrinsic from severe MCD), and infections due to immunoglobulin/complement losses [3][8][11]
- Relapse pattern classification (infrequent, frequent, steroid-dependent) guides long-term immunosuppressive strategy [1]
Treatment Plan
Initial stabilization (ED/acute setting)
- Assess volume status carefully — patients may appear volume-overloaded (edema) but be intravascularly depleted [3][9]
- If hypotensive/hypovolemic: IV albumin 25% (1 g/kg over 2–4 hours) with close monitoring for pulmonary edema [3]
- If euvolemic with significant edema: loop diuretics (furosemide 1–2 mg/kg IV or equivalent); consider co-administration with IV albumin for diuretic resistance [3]
Immunosuppressive therapy
Adults (MCD relapse):
- Infrequent relapse: prednisolone 20–30 mg/day (lower dose than initial treatment may suffice) until proteinuria remits, then taper [2]
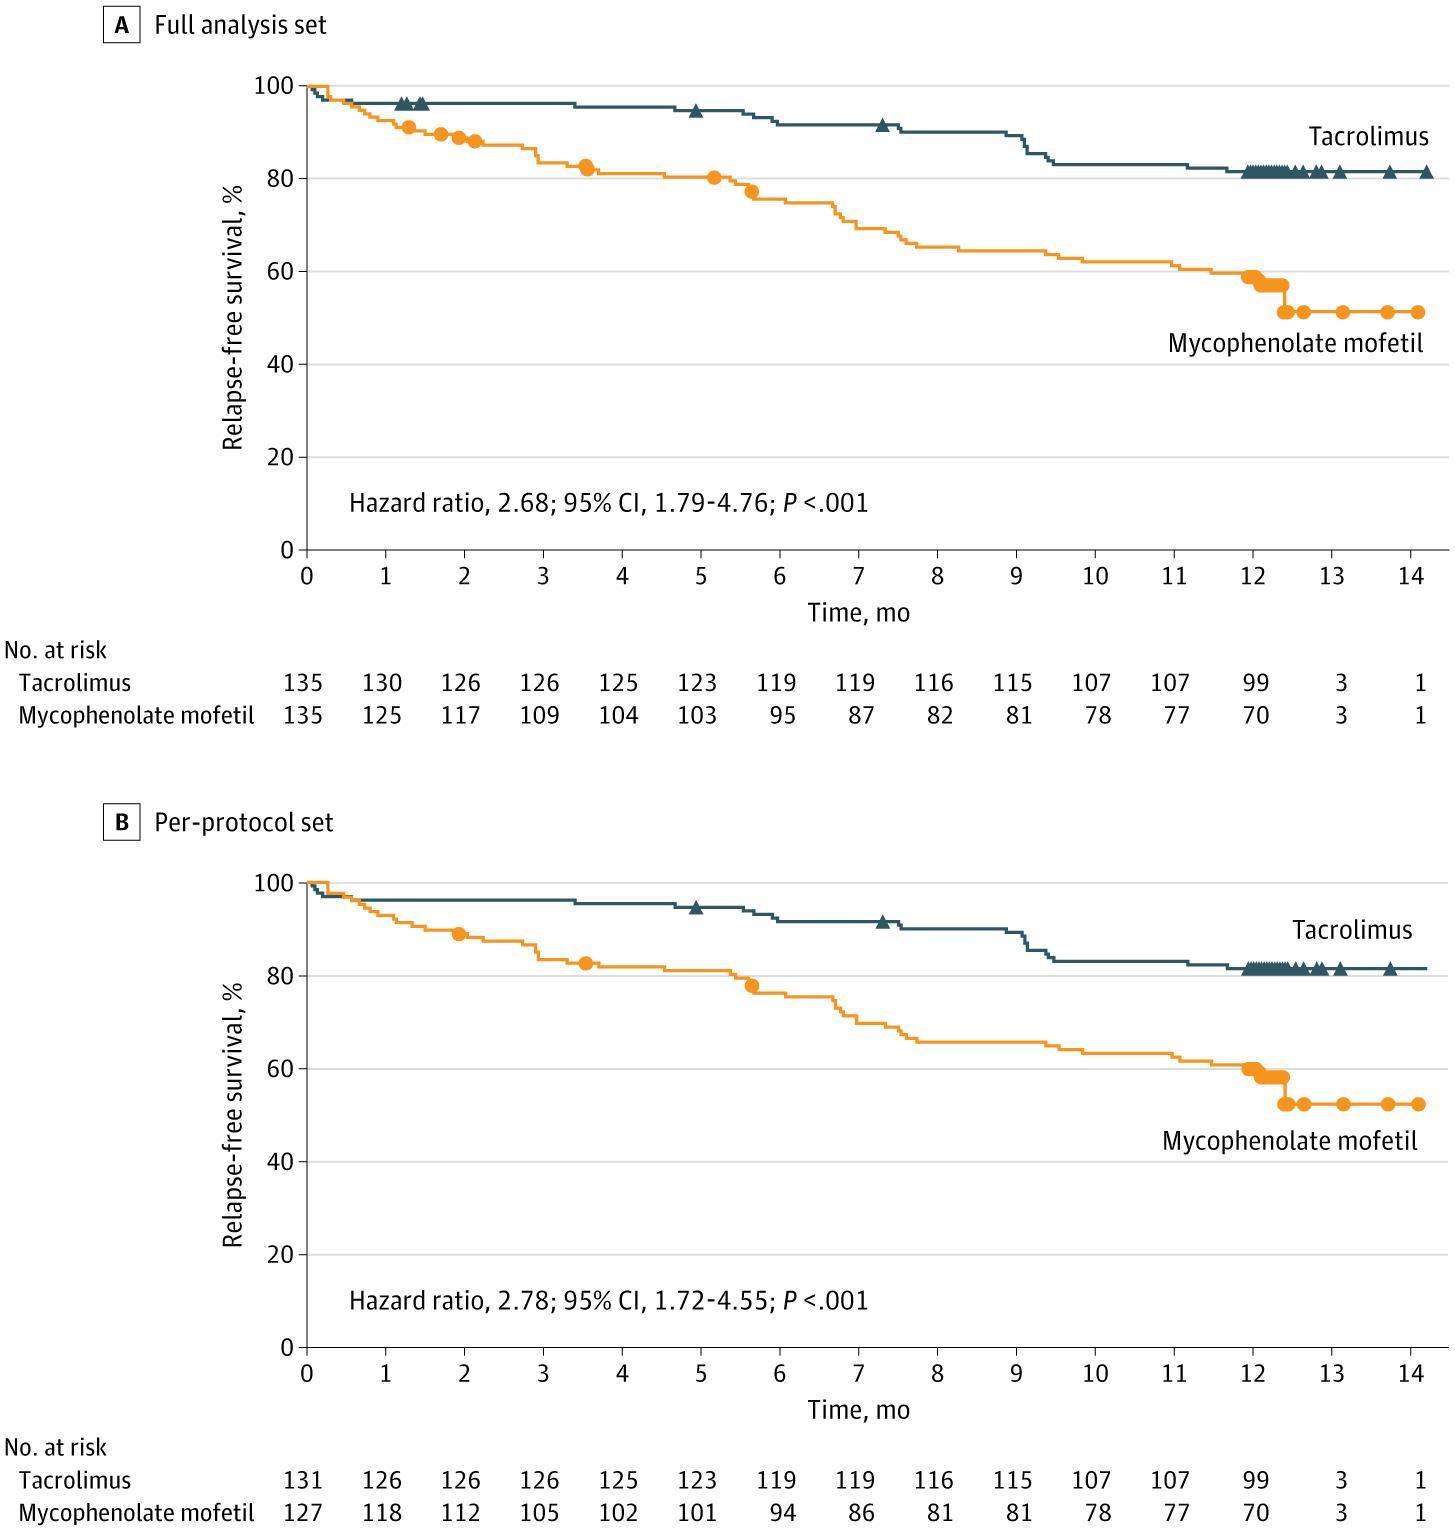
- Frequent relapse/steroid-dependent: glucocorticoid-sparing agents — rituximab, cyclophosphamide, CNIs (cyclosporine/tacrolimus), or MMF per KDIGO 2021 [2][16]
- Rituximab has shown relapse reduction of ~5-fold in observational studies; a 2025 RCT confirmed efficacy for adult FRNS/SDNS [16]
Children (per KDIGO 2025):
- Relapse treatment: prednisone/prednisolone 60 mg/m²/day (max 60 mg) until complete remission for ≥3 days, then 40 mg/m² alternate days (max 40 mg) for 4 weeks [1]
- FRNS/SDNS: glucocorticoid-sparing agents recommended — options include CNIs, cyclophosphamide, levamisole, MMF, or rituximab [1][13]
Supportive care
- Sodium restriction 1.5–2 g/day [2]
- ACEi or ARB for antiproteinuric effect (hold if hypotensive or AKI) [10]
- VTE prophylaxis: mobilization, hydration, avoid central lines; consider anticoagulation (heparin/warfarin) if albumin <2.5 g/dL, especially in membranous nephropathy [2][7]
- Infection vigilance: low threshold for blood cultures and empiric antibiotics if febrile [3]
Disposition
Admission criteria
- Severe/symptomatic edema (respiratory compromise, tense ascites, scrotal edema limiting mobility)
- Hemodynamic instability or signs of hypovolemic shock [3]
- AKI (rising creatinine, oliguria) [8]
- Suspected VTE (DVT, PE, renal vein thrombosis, cerebral venous thrombosis) [2]
- Suspected serious infection (SBP, sepsis, pneumonia) [3]
- Albumin <2.0 g/dL with inability to ensure close outpatient follow-up
- Need for IV diuretics or IV albumin
Discharge criteria
- Stable vital signs, improving edema, adequate oral intake
- Tolerating oral diuretics and steroids
- No evidence of AKI, VTE, or infection
- Reliable follow-up with nephrology arranged
- Patient/family able to perform home urine dipstick monitoring
Observation indications
- Moderate edema requiring IV diuretics with expected rapid response
- Borderline renal function requiring serial monitoring
Specialist consultation triggers
- Nephrology — all flares should have nephrology involvement for immunosuppressive management, consideration of steroid-sparing agents, and biopsy decisions [10]
- Hematology — if VTE occurs or complex anticoagulation decisions
- Infectious disease — atypical or severe infections in immunosuppressed patients
Follow Up / Return Precautions
Follow-up timing
- Nephrology follow-up within 1–2 weeks of discharge or initiation of steroid therapy
- Repeat labs (albumin, creatinine, uPCR) at 1–2 weeks and at 4 weeks to assess response [2]
- If on steroid-sparing agents: drug levels (CNI trough), CBC, LFTs per agent-specific monitoring [3]
Symptoms requiring immediate reassessment
- Worsening edema despite treatment, rapid weight gain (>1 kg/day)
- Decreased urine output or dark/bloody urine
- Fever, abdominal pain (SBP), or signs of infection
- Unilateral leg swelling, chest pain, or sudden dyspnea (VTE/PE)
- Severe headache or neurological changes (cerebral venous thrombosis)
Patient counseling points
- Daily urine dipstick monitoring until remission, then at least twice weekly [3]
- Weigh daily; report weight gain >2 kg in 2–3 days
- Strict sodium restriction during active disease
- Do not abruptly stop steroids — taper as directed
- Avoid NSAIDs and nephrotoxins
- Ensure pneumococcal and influenza vaccinations are up to date [3]
Expected recovery course
- In steroid-sensitive disease, ~50% of adults respond by 4 weeks, with the remainder taking up to 16 weeks [4]
- Children typically respond faster, with most achieving remission within 1–2 weeks of steroid initiation [4]
- Edema resolves as proteinuria remits and albumin normalizes
- Relapse is common (~70–80% in adults with MCD), and patients should be counseled about long-term disease management and the potential need for steroid-sparing agents [4][16]
Images
References
1. KDIGO 2025 Clinical Practoice Guideline for the Mnagement of Nephrotic Syndrome in Children. — Garabed Eknoyan, Norbert Lameire, Wolfgang C. Winkelmayer, et al Kidney Disease: Improving Global Outcomes. 2025.
2. The 2021 Clinical Practice Guideline for the Management of Glomerular Diseases. — Pierre Ronco, Brad Rovin, Detlef Schiandorf, et al Kidney Disease: Improving Global Outcomes. 2021.
3. Childhood Nephrotic Syndrome. — Vivarelli M, Gibson K, Sinha A, Boyer O. Lancet. 2023.
4. Interventions for Minimal Change Disease in Adults With Nephrotic Syndrome. — Azukaitis K, Palmer SC, Strippoli GF, Hodson EM. The Cochrane Database of Systematic Reviews. 2022.
5. Tacrolimus or Mycophenolate Mofetil for Frequently Relapsing or Steroid-Dependent Nephrotic Syndrome. — Wang J, Liu F, Yan W, et al. JAMA Pediatrics. 2025.
6. Idiopathic Nephrotic Syndrome in Children. — Noone DG, Iijima K, Parekh R. Lancet. 2018.
7. KDOQI US Commentary on the 2021 KDIGO Clinical Practice Guideline for the Management of Glomerular Diseases. — Beck LH, Ayoub I, Caster D, et al. American Journal of Kidney Diseases : The Official Journal of the National Kidney Foundation. 2023.
8. Acute Kidney Injury Complicating Nephrotic Syndrome of Minimal Change Disease. — Meyrier A, Niaudet P. Kidney International. 2018.
9. The Nephrotic Syndrome. — Orth SR, Ritz E. The New England Journal of Medicine. 1998.
10. Diagnosis and Management of Nephrotic Syndrome in Adults. — Kodner C. American Family Physician. 2016.
11. Nephrotic Syndrome: Pathophysiology and Consequences. — Claudio P, Gabriella M. Journal of Nephrology. 2023.
12. Risk Factors of Venous Thromboembolism in Patients With Nephrotic Syndrome: A Retrospective Cohort Study. — Shinkawa K, Yoshida S, Seki T, Yanagita M, Kawakami K. Nephrology, Dialysis, Transplantation : Official Publication of the European Dialysis and Transplant Association - European Renal Association. 2020.
13. KDIGO 2025 Clinical Practice Guideline for the Management of Nephrotic Syndrome in Children. — Floege J, Gibson KL, Vivarelli M, et al. Kidney International. 2025.
14. Membranous Nephropathy. — Katie Trinh, Bhadran Bose Evidence-Based Nephrology, 2nd Edition. 2022.
15. Nephrotic Syndrome in Adults: Diagnosis and Management. — Kodner C. American Family Physician. 2009.
16. Rituximab for Relapsing Nephrotic Syndrome in Adults. — Isaka Y, Sakaguchi Y, Shinzawa M, et al. The Journal of the American Medical Association. 2025.
Figures
More from Deep Dive
Reviewed by Dr. Lucas Mastropaolo. SymptomDx is an educational tool for medical professionals — it does not replace clinical judgment. Verify all clinical data and drug dosages with authoritative sources.